



Label-free quantification (LFQ) fits biomedical research when the goal is relative same-protein discovery across independent patient, model, or treatment samples without isotopic or isobaric labeling, and when enrollment, batching, or scarce material makes a closed multiplex kit impractical. Typical applications include diseased versus control tissue contrasts for pathway hypotheses, serum or urine profiling for candidate biomarker lists, drug- or treatment-induced proteome shifts in models, and exploratory cohort subtyping by protein patterns. LFQ does not by itself deliver diagnostic cutoffs, regulatory-grade assays, or absolute concentrations; those need targeted validation after discovery (Cox et al. 2014).
Researchers who already have defined samples, comparison groups, or a specific biomedical objective can also review the MtoZ Biolabs Label-Free Quantitative Proteomics Service and Deep DIA Proteomics Service for project-specific feasibility and analysis planning.
Biomedical Application Areas Where LFQ Is Commonly Used
Application pattern |
What LFQ is used for |
What the result supports |
|---|---|---|
Disease mechanism studies |
Case-control or state contrasts in tissue or cell models |
Relative protein shifts linked to pathway follow-up |
Biofluid biomarker screening |
Large panels in serum, plasma, urine, or CSF |
Candidate marker lists for later targeted testing |
Pharmacology and toxicology |
Pre- versus post-treatment or dose arms in models |
Relative response signatures, not approved drug labels |
Exploratory subtyping |
Clustering on protein expression across a cohort |
Hypothesis for stratification, not clinical staging alone |
Scarce or complex specimens |
Biopsies, exosomes, stem cells, low-input lysates |
Discovery when labeling chemistry is risky or wasteful |
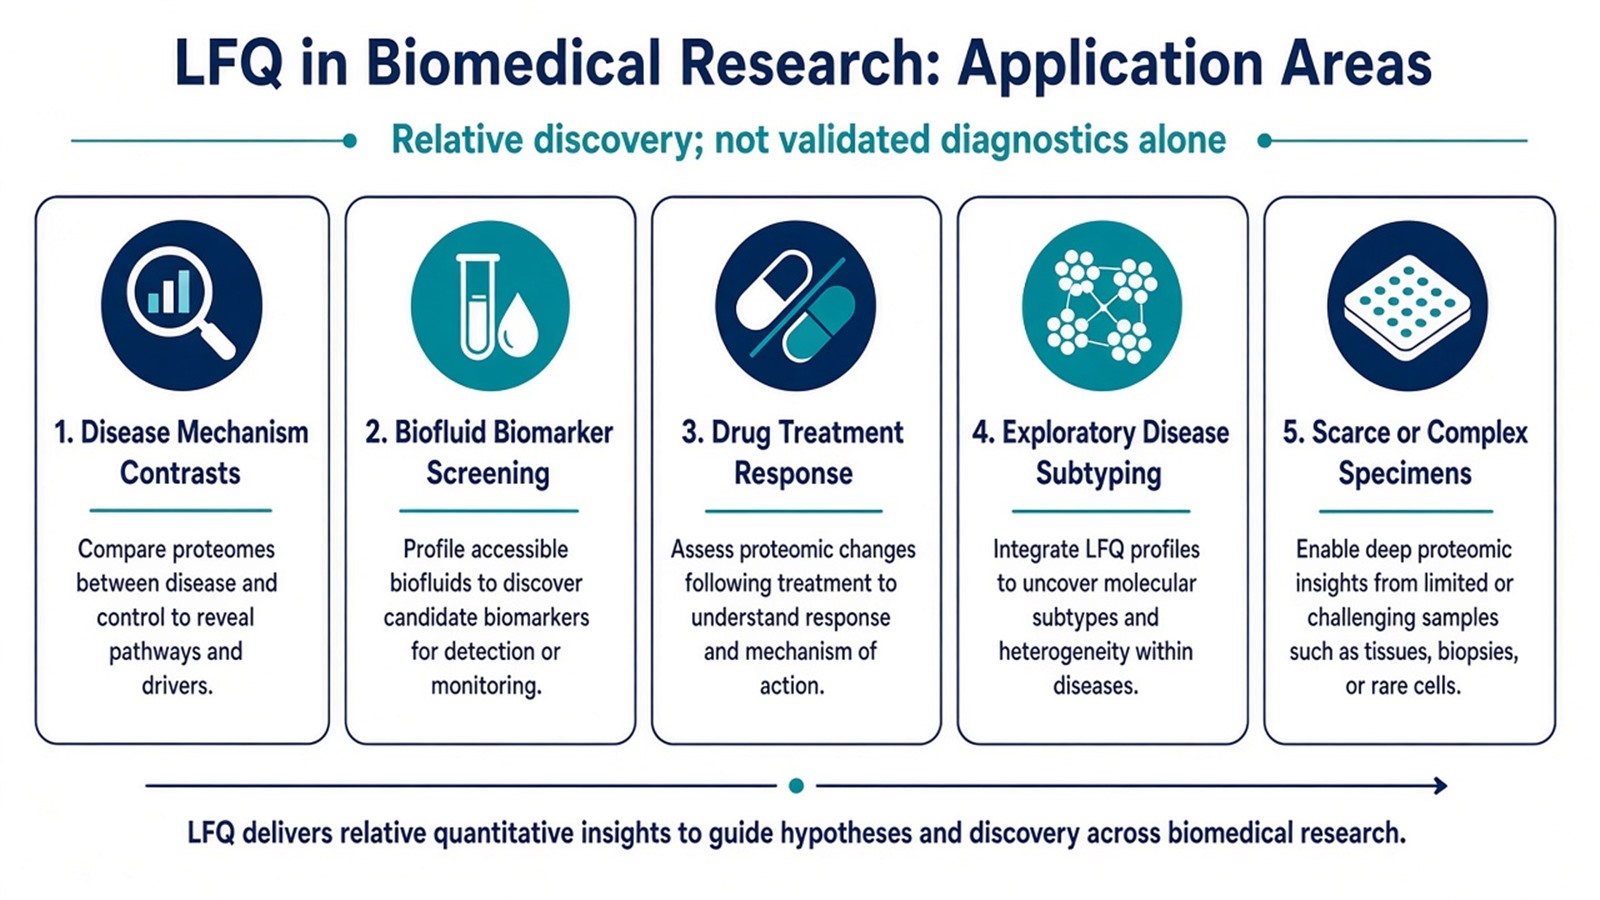
Figure 1. LFQ in biomedicine is used for relative discovery across independent samples; each application still needs a matched design and QC plan.
LFQ application value is relative discovery inside a coherent study, not automatic translation to the clinic without a separate validation path.
How LFQ Is Applied in Practice (Without Confusing the Claim)
LFQ in biomedicine runs as unlabeled bottom-up proteomics: each sample is digested and acquired as its own liquid chromatography-tandem mass spectrometry (LC-MS/MS) injection. Peptide identities come from database search. Quantitative values usually come from MS1 peak areas in data-dependent acquisition (DDA) workflows such as MaxLFQ, or from fragment chromatograms in unlabeled data-independent acquisition (DIA) (Gillet et al. 2012). Comparability is rebuilt by alignment, normalization, and batch-aware QC across runs.
That execution model explains why LFQ suits longitudinal cohorts, multi-batch clinical collections, and studies that may add samples later under a compatible regime. It also explains why run order, digestion consistency, and instrument drift are part of the method. For step-by-step operations, researchers can refer to What Is Label-Free Analysis? LFQ Principles, Workflow, Advantages, and Limitations. For global shotgun strategy framing, see Label-Free Shotgun Proteomics as a Strategy for Global Protein Quantification.
Judgment Criteria: When LFQ Fits a Biomedical Question
Study need |
LFQ often fits |
Reassess before committing |
|---|---|---|
Quantitative claim |
Relative same-protein discovery across groups |
Absolute concentration or diagnostic cutoff |
Sample plan |
Independent injections; enrollment may continue |
All contrasts must share one TMT plex |
Matrix |
Labeling chemistry is risky or impractical |
Clean amine labeling and closed plex are preferred |
Throughput |
Many biofluid or model samples under one QC plan |
Only a short closed peptide list matters |
Follow-up path |
Open list can later enter PRM, MRM, or immunoassay |
Expect discovery alone to satisfy regulatory readout |
Prefer LFQ when biomedical samples must stay unlabeled and the question is open relative discovery. Prefer tandem mass tag (TMT) multiplex labeling when every planned channel fits one kit and same-run reporter comparison is the priority. Prefer unlabeled DIA inside LFQ when cohort completeness matters more than DDA stochastic missingness. Prefer DDA-LFQ when identification clarity, MaxLFQ tooling, or library building is central. Prefer targeted assays when the panel is closed or absolute units are required.
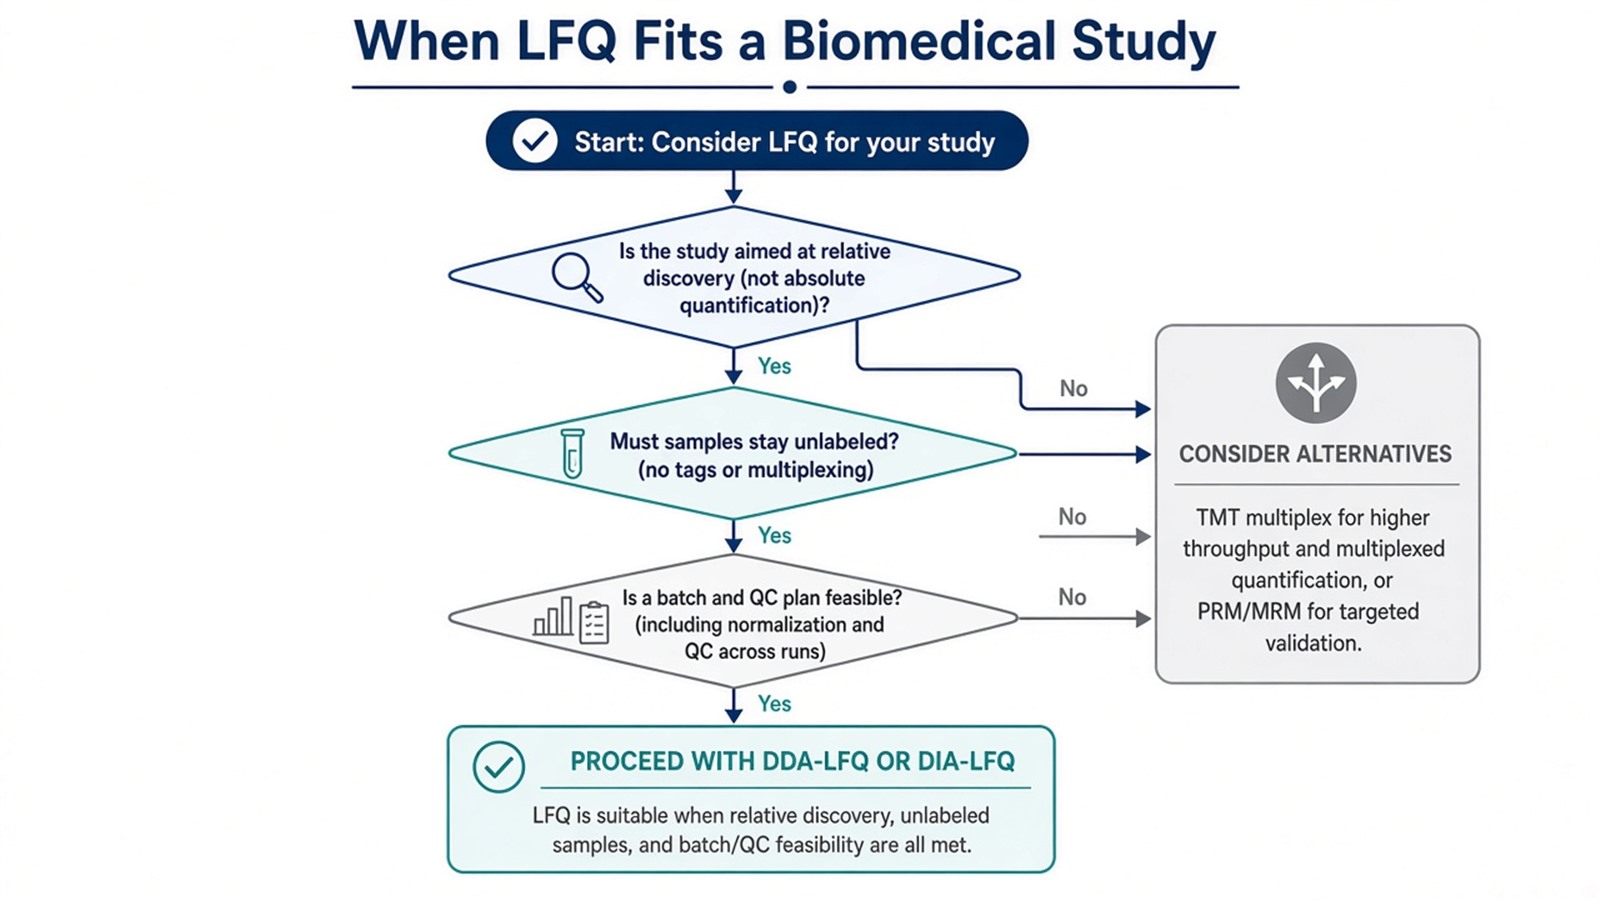
Figure 2. Match the biomedical question to the claim: LFQ for relative unlabeled discovery, or change strategy when multiplex labeling or targeted validation dominates.
For labeling versus unlabeled selection, see TMT vs Label Free Quantitative Proteomics. For acquisition choice inside LFQ, see DIA vs DDA Proteomics: Key Differences and Applications Explained. For normalization choices that affect biomedical batch structure, see How to Normalize Data in Label-Free Quantitative Proteomics?.
Limits and Boundaries for Biomedical Use
Ordinary LFQ intensities remain relative unless matched standards and a calibration model are added. Missing values, especially under DDA, can weaken sparse biofluid signals. Batch effects across collection sites or run weeks can mimic biology if run order is confounded. Pathway enrichment from a differential list shows overrepresentation relative to the quantified background; it does not prove pathway activity in patients.
Biomarker discovery with LFQ produces candidates and effect directions inside the studied cohort. Clinical deployment needs independent cohorts, predefined endpoints, and usually targeted or immunoassay confirmation. Subtyping from unsupervised clustering is exploratory until reproduced with prespecified rules. Low-input success still depends on cleanup, loading, and instrument time, not on the label-free name alone.
Diagnostic cutoffs, companion diagnostic claims, and absolute stoichiometry sit outside default LFQ reporting unless a separately validated assay framework is in place.
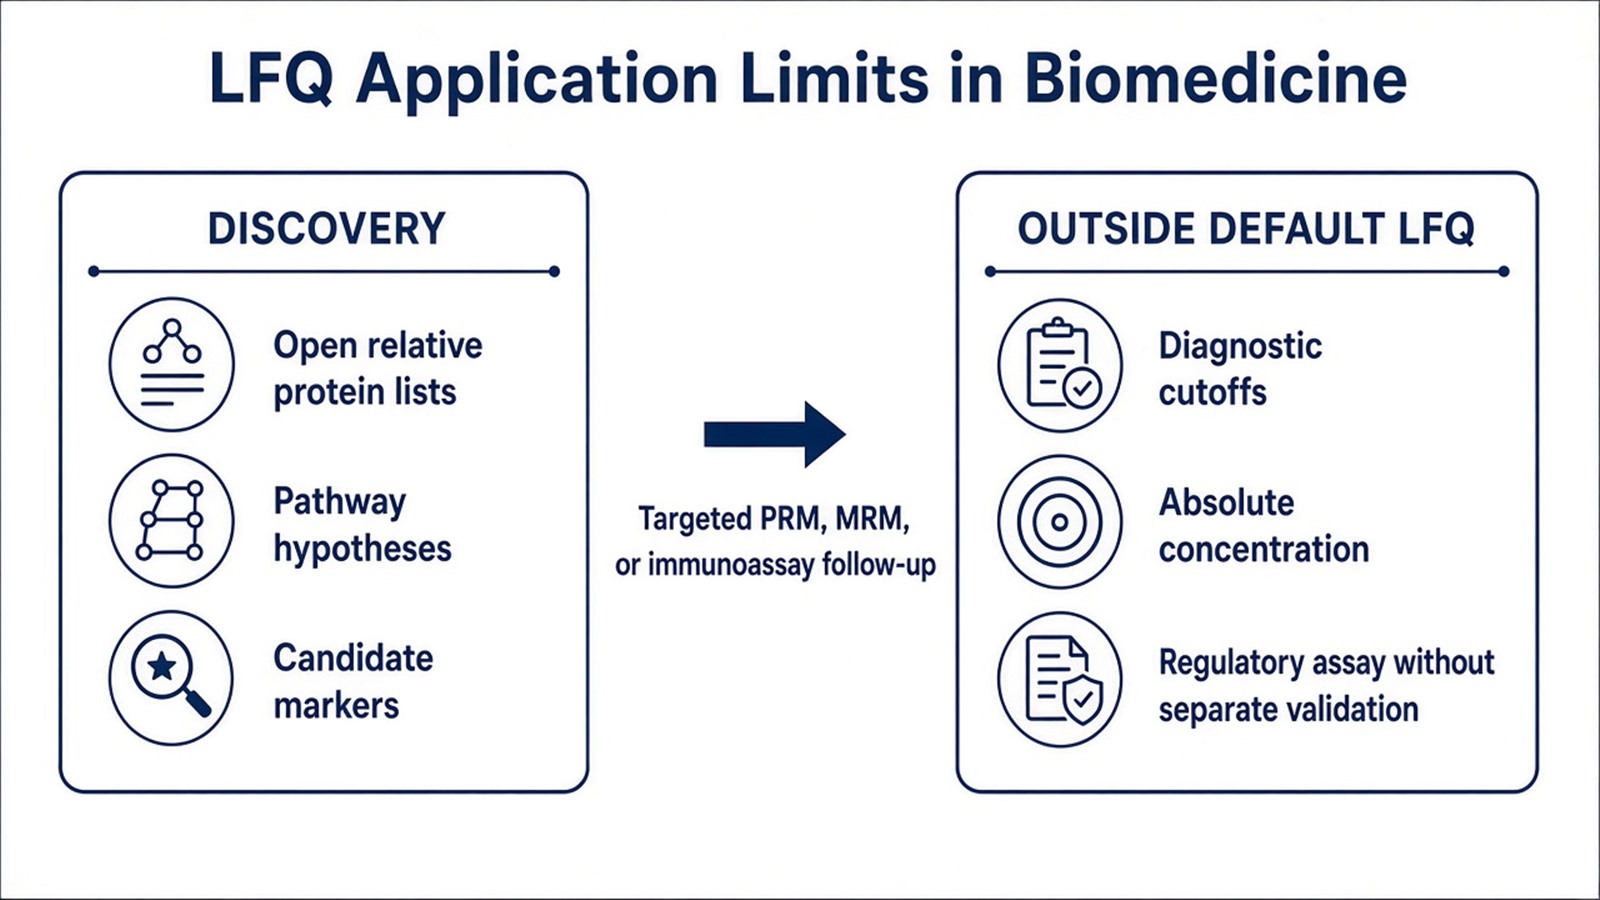
Figure 3. LFQ supports discovery and hypothesis in biomedicine; diagnostic, absolute, and regulatory claims need a defined validation layer.
For design-level trade-offs, see Advantages and Disadvantages of Label-Free Quantitative Proteomics. For unlabeled DIA service options, see Label-Free DIA Quantitative Proteomics.
Application Notes by Biomedical Setting
Mechanism studies in tissue or primary cells use LFQ when contrasts are defined and preparation can be matched. Biofluid screening uses LFQ when many samples must enter under randomization and QC pools, accepting that low-abundance proteins may stay missing without enrichment or targeted follow-up. Drug and treatment studies use LFQ when multiple time points or doses are compared as relative shifts, with vehicle and batch controls explicit in the design. Precision-medicine subtyping uses LFQ when protein patterns are combined with clinical metadata for exploratory groups, not as a standalone treatment assignment rule.
Once the biomedical claim, sample plan, acquisition mode, and QC rules are defined, the project can be scoped as a biomedical LFQ study. Researchers can review the MtoZ Biolabs Label-Free Quantitative Proteomics Service for sample evaluation and workflow planning, and the Deep DIA Proteomics Service when unlabeled DIA is part of the design. For analysis software paths after acquisition, see Essential Analysis Tools for Label-Free Proteomics: A Comprehensive Review of MaxQuant and DIA-NN.
Frequently Asked Questions
1. Is LFQ widely used in clinical biomarker research?
Yes, for relative profiling and candidate discovery in controlled cohorts. It is not, by itself, a validated clinical assay platform without follow-up confirmation.
2. Can LFQ replace TMT in multi-arm treatment panels?
Not automatically. TMT can help when all arms fit one multiplex kit and same-run comparison is critical. LFQ fits when samples stay independent or enrollment is open.
3. Which acquisition mode should biomedical LFQ use?
DDA-LFQ is common for MaxLFQ workflows and identification-centric studies. Unlabeled DIA often suits larger cohorts where missing-value control matters. The choice follows the claim and QC plan, not a universal ranking.
4. Does LFQ work on scarce patient material?
It can, when digestion and cleanup are controlled and expectations match input limits. Labeling steps are avoided, but low input still constrains depth and missingness.
5. Can LFQ results support precision medicine decisions directly?
LFQ can support exploratory subtyping and hypothesis generation. Treatment decisions that need validated markers should rely on targeted or clinical assays built after discovery.
Reference
- J. Cox, M.Y. Hein, C.A. Luber, et al. (2014). Accurate proteome-wide label-free quantification by delayed normalization and maximal peptide ratio extraction, termed MaxLFQ. Mol. Cell. Proteomics, 13, 2513-2526. https://doi.org/10.1074/mcp.M113.031591
- L.C. Gillet, P. Navarro, S. Tate, et al. (2012). Targeted data extraction of the MS/MS spectra generated by data-independent acquisition: a new concept for consistent and accurate proteome analysis. Mol. Cell. Proteomics, 11, O111.016717. https://doi.org/10.1074/mcp.M111.016717
