



A biomedical project usually needs protein quantification when the hypothesis is about protein abundance change: a disease model versus control, a treated sample versus vehicle, or a short candidate list that must be remeasured in a new digest. The importance of the measurement is the claim it can support in that design. LC-MS/MS relative quantification can show same-protein differences inside one study after extraction, digestion, and a declared contrast. It does not diagnose disease, assign therapy, or prove that a pathway was switched on. Application planning starts from the claim, the matrix, and whether the protein list is still open.
Which Biomedical Questions Need Protein Quantification
Protein quantification is worth doing when the experimental factor is expected to change protein amount or occupancy, and when those changes must be compared across a defined cohort. Typical questions are whether a genetic or disease model alters a proteome relative to its control, whether a compound changes target-pathway proteins after a stated exposure, and whether nominated peptides remain detectable in an independent sample set. Transcript levels, enzyme activity, and antibody blots answer adjacent questions. They do not replace a peptide-level matrix when the study needs many proteins without a preselected antibody panel.
The application also has to match the output type. Discovery quantification, whether unlabeled DDA, unlabeled DIA, or TMT, produces a relative protein matrix for an open or semi-open list. Targeted PRM or MRM produces peak areas for predefined peptides. Mixing those aims in one sentence, for example calling a discovery list a diagnostic panel, creates a claim the dataset cannot carry. Research comparisons and CMC-supporting characterization are the intended uses of this workflow. In-vitro diagnostic testing and clinical decision-making sit outside it.
How Common Applications Map to MS Capabilities
Biomedical use-cases differ in whether the protein list is open, how many samples must stay comparable, and whether an amount or a fold change is required.
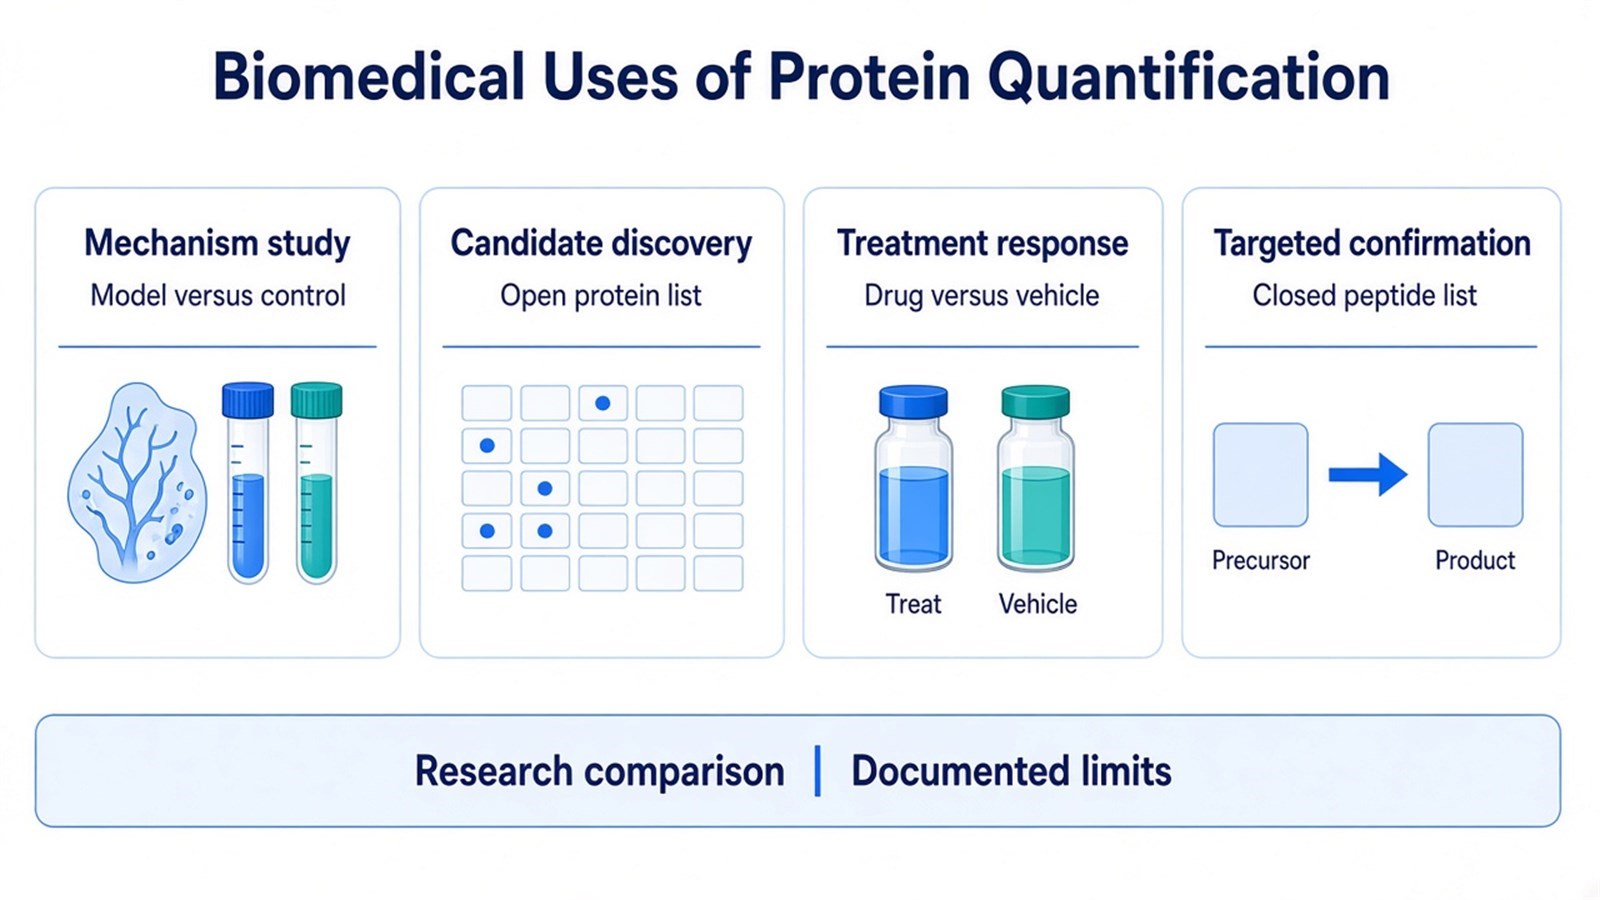
Figure 1. Protein quantification in biomedical research is used for mechanism comparison, candidate discovery, treatment-response profiling, and targeted confirmation of a closed peptide list.
Mechanism and model comparison
Cell, tissue, or organism models are compared so that protein-level consequences of a genotype, injury, or disease-like state can be described. Unlabeled discovery routes scale when groups are added over time. TMT is often useful when a closed sample set must be labeled and acquired together. The result can support a statement that named proteins changed between the modeled states under the stated processing. It cannot assign those proteins as causes of the phenotype without perturbation or orthogonal evidence. Sample anatomy, dissection timing, and freeze history still limit the matrix, as they do in any quantitative proteomics study.
Candidate protein research
Biomedical groups often want proteins that distinguish cases from controls in tissue or biofluid. Discovery LC-MS/MS can rank same-protein differences and produce a candidate list for the present cohort (Geyer et al. 2017). Plasma and serum remain dominated by high-abundance proteins, so depletion, extra input, or a later targeted assay may be required before low-abundance candidates are credible. A candidate from one discovery experiment is a hypothesis. Replication in an independent set, and usually a targeted assay with matrix-matched transitions, are separate studies. Diagnostic sensitivity, specificity, and intended-use claims are outside this research workflow.
Treatment and perturbation response
Drug, ligand, or knockdown studies ask which proteins change after a defined dose and time. Discovery quantification can profile the measurable proteome before and after treatment. Targeted assays can follow a preselected pharmacodynamic panel across a time course. The result can support treatment-associated protein change in that model, including proteins that move with the intended target pathway. It does not establish clinical efficacy, safety, or dose selection. Vehicle and treated samples must be processed in interleaved order so that run batch is not identical to treatment.
Targeted confirmation is the application that starts after names exist. PRM or MRM remeasures chosen peptides with fragment evidence that was scheduled in advance. Absolute amount still needs a matched isotope standard. Confirmation in a new digest does not inherit the discovery fold change automatically.
Study Design Parameters That Make an Application Defensible
Application quality is set before the first injection. The contrast (model versus control, treated versus vehicle, baseline versus follow-up) has to be named, and biological replicates have to belong to that contrast. Technical injections describe process noise. They do not power a between-donor biomedical claim.
Matrix and input decide depth. Tissue mechanism studies often start from tens of milligrams of soft tissue. Cell treatments are planned around a pellet that yields enough digest for the chosen route. Plasma candidate work must record anticoagulant, hemolysis, and whether depletion will be used. Buffer recipes for client lysates have to be disclosed, because residual SDS or polymer additives block later peptide quantification. Researchers can refer to The Importance and Common Methods of Protein Quantification Analysis for more detailed sample-planning guidance.
Method parameters should follow the application. An open biomedical screen with many independent samples usually fits unlabeled DDA-based label-free or unlabeled DIA. A small, simultaneous comparison can fit a TMT set acquired in DDA so that reporter ions can be read. In MtoZ Biolabs offerings, those pairings are typical service routes; DIA remains an acquisition mode, and TMT remains a labeling choice. Identification FDR, unique-peptide rules, normalization, and missing-value handling must be declared with the application claim, because a later pathway story is only as strong as that matrix. Researchers can refer to How to Analyze Quantitative Proteomics Data for how those analysis rules are set before a contrast is tested.
Claims That Quantitative Proteomics Cannot Carry
A same-protein fold change in one cohort does not transfer to a diagnostic cutoff. Enrichment of a Gene Ontology or KEGG term supports overrepresentation in the tested list relative to a quantified background. It does not prove pathway activity or disease mechanism (Aebersold and Mann 2016). Predicted interaction networks do not show that a complex formed in the present samples.
Antibody assays remain useful when a single epitope and a validated antibody already answer the biomedical question. They do not generate a proteome-wide matrix and they do not convert an MS candidate into a clinical test. Multi-omics overlays require matched sample identity; an mRNA discordance is a common biological outcome.
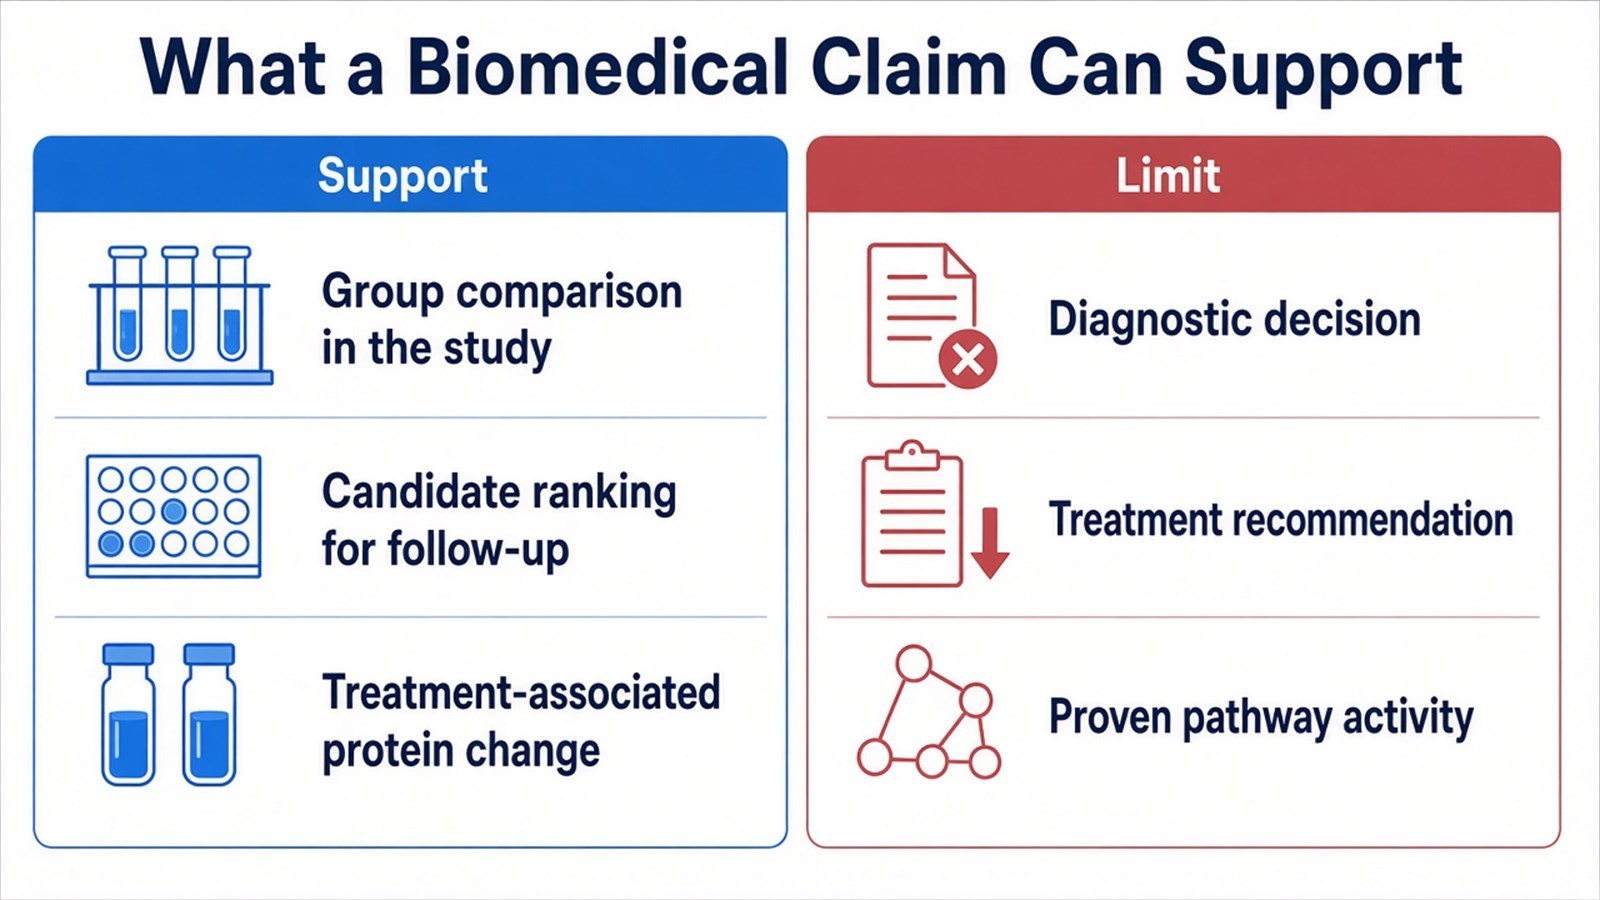
Figure 2. Biomedical protein quantification can support group comparison, candidate ranking, and treatment-associated change in the study; diagnostic decisions, treatment recommendations, and proven pathway activity remain outside the result.
Choosing a Project Path by Application
Lock the application, the allowed claim, and the quantitative route before samples are queued.
Biomedical application |
Quantitative route often used |
Result that can be defended |
Reassess before locking |
|---|---|---|---|
Mechanism or disease-model comparison |
Unlabeled discovery or TMT on a closed set |
Same-protein relative change between modeled groups |
Phenotype causation inferred from the protein list alone |
Candidate discovery in tissue or biofluid |
Unlabeled discovery, with depletion planned for plasma if needed |
Ranked candidates in the present cohort |
Calling the list a diagnostic panel |
Treatment or perturbation response |
Discovery profile, or a predefined targeted panel |
Treatment-associated protein change at the stated dose and time |
Efficacy, safety, or clinical dose |
Independent confirmation of named proteins |
PRM or MRM, with SIS if amount is required |
Peptide-level confirmation in a new digest |
Re-searching the original discovery files as validation |
Amount or concentration of a known target |
Targeted assay plus matched isotope standard |
Peptide amount under the digest conditions used |
Copy-number ranking across different proteins |
If the protein list is still open, keep the project on discovery quantification and size replicates to the contrast. If names already exist and the biomedical claim is confirmation, stop expanding discovery figures and design a targeted assay. Researchers can refer to Advantages and Disadvantages of MRM/PRM Techniques when that confirmation route still needs to be chosen. If the intended sentence in the paper is a clinical decision, the present LC-MS/MS research workflow is the wrong instrument for that sentence.
Researchers can review the MtoZ Biolabs Quantitative Proteomics Service for project-specific sample evaluation, feasibility assessment, and workflow planning.
Frequently Asked Questions
1. Can protein quantification be used to diagnose disease?
A research comparison can show protein differences between defined groups in the study. Diagnosis requires an intended-use assay, clinical validation, and regulatory authorization that this research workflow does not provide. Keep diagnostic language out of the results section.
2. Is one discovery experiment enough to report a biomarker?
One discovery matrix can nominate candidates. A biomarker research story still needs a stated cohort, replication, and usually targeted remeasurement in the relevant matrix. Publication of a ranked list is not the same as a qualified biomarker.
3. Does a treatment-response proteome prove that a drug works?
It can show which measured proteins changed after the treatment in that model. Clinical benefit, toxicity, and dose selection need dedicated pharmacology and safety studies. Interleave treated and control samples so that batch does not copy the treatment factor.
4. When should targeted MS follow a biomedical discovery study?
Use targeted MS when the protein list is closed, the same peptides must be compared across many samples, or an amount claim is required. Keep discovery processing only while new names are still the goal.
5. How should ELISA or Western blot sit beside LC-MS/MS in the same project?
Use the antibody assay when a single known epitope is the endpoint and the antibody is validated for that matrix. Use LC-MS/MS when many proteins must be compared without depending on antibody availability. The two readouts quantify different molecular features and should be reported as such.
MtoZ Biolabs can provide quantitative proteomics analysis for biomedical research applications, including mechanism comparison, candidate discovery, treatment-response profiling, and targeted confirmation of predefined peptides.
If further evaluation of study design, sample matrix, allowed claims, or discovery versus targeted routing is needed, project details can be submitted for a feasibility review.
